AI in health plans, where it pays
Plans often catalog 200 to 300 AI use cases. Only three or four move a P&L.
When AI pays in a health plan
AI pays in a health plan when a workflow actually changes and a finance partner can see where the value landed.
Most payers adopt AI by collecting use cases. A list of 200 to 300 candidates looks like progress, and the leadership team reaches for a project management office to run it. Yet payer executives generally recognize that only a few initiatives, perhaps three or four, will meaningfully move a supporting P&L. What is missing is a way to pick them and see them through.
This guide covers where your plan sits on the AI maturity ladder, the operating model that turns use cases into results, where AI has already paid in network management, the rules to set first, and how to start. It draws on 3Pillars' AI Transformation Advisory practice, which follows the same lifecycle as any growth project in the Value Architecture: quantify the opportunity, prove it works, accelerate adoption, realize outcomes, and scale what is working.
Find your rung before you buy
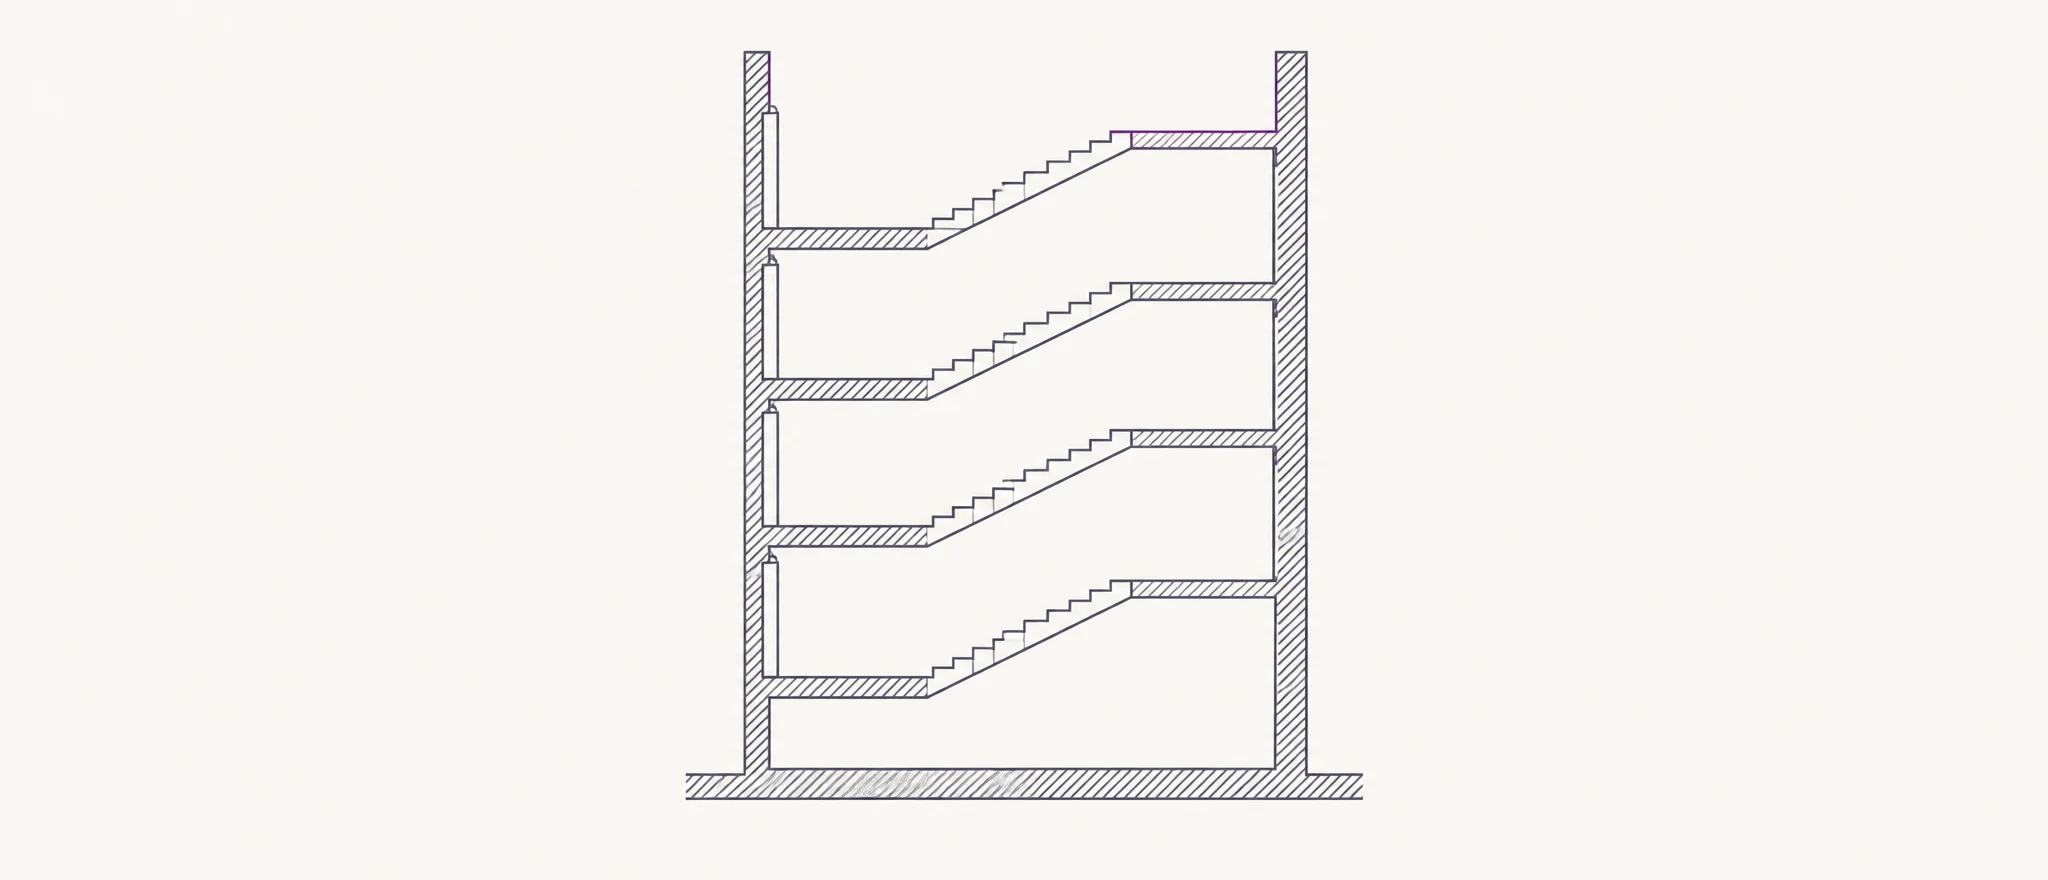
AI maturity is how deeply AI is absorbed into the way work gets done, not the tools licensed or the pilots underway. Most healthcare organizations sit between Levels 0 and 1 while buying as though they were at Level 3.
The plans that waste money on AI almost always try to skip a level.
Level 4 · Future state
AI-native
Designed AI-first from day one.
Emerging at digital-native firms outside healthcare. A long horizon for any healthcare organization today.
Level 3 · Decision partner
In the operating model
AI shapes core decisions and operations.
Models tuned to the organization. Governance, data, and talent redesigned to match.
Level 2 · Process operator
In the workflow
AI embedded in defined processes.
Off-the-shelf, healthcare-specialized vendor, or custom models by task. Workflow redesigned around the model.
The first rung where value becomes measurable
Level 1 · Workforce amplifier
In the toolkit
Approved AI tools rolled out to teams.
Real productivity gains, but the workflow has not changed. Same work, faster.
Most healthcare organizations live here
Level 0 · Personal assistant
On the side
Individuals using consumer AI tools on their own.
No org policy. No workflow integration. Often invisible to compliance.
Two questions place you on the ladder
Has any workflow actually been redesigned around a model, or has the existing work simply been accelerated?
Could you show a finance partner where the value landed?
A plan that cannot answer the first is at Level 1 or below, whatever it has licensed. The levels are a diagnostic frame, not a benchmark or a scoring method. Read the five levels of AI maturity in healthcare
Run AI from a strategy office, not a PMO
AI work is exploratory, and its value is realized only when a change in workflow takes hold. A strategic management office (SMO) is a lightweight, forward-deployed strategy-and-execution function built for that kind of work.
It is business-led. Only the executives who own the business verticals can authorize the workflow changes most AI initiatives depend on, so the board and several executives stay engaged.
Why AI transformation needs a strategic management officeA project management office
A strategic management office
PMO: Tracks the work it is given.
SMO: Decides which few initiatives are worth doing.
PMO: Fits a fixed scope delivered on time and on budget.
SMO: Fits exploratory work whose scope shifts as understanding grows.
PMO: Manages from a distance.
SMO: Sits inside the work, with AI agents alongside experienced operators.
PMO: Reports progress.
SMO: Holds realized value against what was forecast.
The model at work
A supply chain data company launching two healthcare lines of business at once runs on an agentic PMO 3Pillars built on Claude Cowork. It preps every meeting, turns each call into tracked tasks, decisions and risks, and drafts the customer, agency and state updates. A traditional PMO would have needed one to three staff per workstream.
Read the agentic PMO case study2 FTEs
Replaced
about $300K a year in loaded cost
8–10 → 1–2
Hours a week of senior time
on board and customer materials
4–8 hrs
Given back per team member a week
meeting and coordination load
152
Meetings processed in 62 runs
May 15 to September 14, 2026
Where it pays: network management
In health plan terms, payer contracting is network management. 3Pillars modeled a contracting engine on how a regional health plan runs its contracting shop, then built it on Claude for a PE-backed behavioral health provider group with payer contracts across Medicaid, Medicare Advantage and commercial lines.
Agents read more than 1,000 documents and normalized 82 contracts into one 42-field record with CPT-level rates. Analysis agents then wrote seven briefs, from renewal risk and payer mix to rates against 2026 Medicare and value-based terms.
$7M
Opportunity identified
across the full contract book
3 weeks
Standing start to live
in production on the live contract book, April to May 2026
40+ → 8
Contract ops hours a month
with no added contracting staff
12+ mo
Renewal visibility
was reactive; 3 contracts found past their notice deadline
On the 8 priority payers alone, about $25M of trailing revenue, the conservative annualized upside is $2.0M to $4.5M+, or 8% to 18%.
Write the rules before the rollout
In regulated healthcare, untrained use of a general-purpose model carries specific risks: protected health information in a prompt, confidential IP in a chat, a claim that outruns the regulatory posture. When 3Pillars trained a MedTech leadership team on Claude, these four rules were written on the first day and adopted on the second.
No protected health information in prompts
Patient and pilot-site data never goes into a chat, a skill or a scheduled run.
IP and confidentiality rules
An inventory sets which documents, data and systems the model can and cannot touch.
Claims held to the regulatory standard
Anything the model drafts about what a product does or proves meets the same bar as the regulatory submission.
Decisions stay with people
The model drafts, ranks and summarizes. Leaders decide.
Someone has to own realized value
Rules need an owner, and so does the return. A fractional chief AI officer is a senior operator who owns the realized ROI of AI from inside the business, alongside an AI leader you already have or in the seat until you hire one.
Start with an AI Leverage Map
A first read of how work moves through your plan, across teams, systems and decision points. It ends in a prioritized roadmap with quantified value cases, so you know which three or four initiatives to fund.
See AI Transformation AdvisoryAI Leverage Map
Typically 1 to 2 weeks
A structured read of operational readiness and the highest-value opportunities, based on how work moves across teams, systems, and decision points. It produces a prioritized roadmap with quantified value cases.
AI Enablement Planning
Typically 2 to 4 weeks
Current state workflow mapping, operating model and governance design, adoption planning, and the KPI and measurement frameworks that ready a specific AI initiative, or a portfolio of AI investments, to execute.
Fractional AI Leadership and Stewardship
Retainer basis
Embedded fractional AI leadership: a senior operator or program lead who owns realized ROI, with continuous oversight, optimization, and value tracking so AI investments compound over time rather than stall after launch. It runs alongside your build team or ours.
AI Build
Outcome and ROI-based
3Pillars stands up the solution with its own delivery bench: your data with a frontier model, or a private model deployed in your environment. Stewardship stays embedded, and you own the code, playbooks, and results.
Questions about AI in health plans
Where does AI pay off first for a health plan?
In the few initiatives that change a workflow tied to a P&L. Health plans commonly catalog 200 to 300 candidate AI use cases, yet only three or four meaningfully move a P&L. Network management is one example: 3Pillars modeled a contracting engine on how a regional health plan runs its contracting shop, and for a PE-backed provider group its agents read 1,000+ payer contract documents and identified a $7M opportunity in three weeks.
What is an AI maturity model for healthcare?
A ladder that describes how deeply AI is absorbed into how work gets done, not an inventory of tools licensed. 3Pillars uses five levels: on the side, in the toolkit, in the workflow, in the operating model, and AI-native. Most healthcare organizations sit between Levels 0 and 1. Value becomes measurable at Level 2, the first rung where the workflow is redesigned around the model.
Why does AI transformation need a strategic management office instead of a PMO?
A PMO is built to track the work it is given, not to decide what is worth doing, and it fits fixed-scope work. AI work is exploratory and its value is realized only when a workflow changes. A strategic management office is a lightweight, forward-deployed strategy-and-execution function that concentrates on the few initiatives that matter and holds realized value against forecast.
Who helps health plans with AI strategy and adoption?
3Pillars Solutions is a healthcare growth advisory firm that works with payers, healthtech and medtech innovators, and investors. Its AI Transformation Advisory practice helps healthcare organizations adopt, govern, and measure AI, through the AI Leverage Map, AI Enablement Planning, Fractional AI Leadership and Stewardship, and AI Build. Its senior advisor network pairs healthcare operators and executives with AI and data science experts.
How fast do we see something real?
Weeks, not quarters, for the first read. The AI Leverage Map runs in one to two weeks and Enablement Planning in two to four, so you have a prioritized, quantified roadmap early. From there, most operational AI workflows reach first measurable value within a quarter, depending on the use case and how ready the data is.
Our data is a mess. Do we need to fix that first?
No. Drawing the data map, what exists, what condition it is in, and what it blocks, is part of the Leverage Map's first read. Some of the highest-value workflows run on imperfect data. What matters is knowing which gaps are worth closing before you invest in closing them.
How are you different from an AI agent firm?
An agent firm brings the agents and asks where to point them. We work the other way: an operator maps how work actually moves through your organization, attaches a number to each opportunity, and only then decides what to build, or whether to build at all. We are healthcare-native, so that judgment is grounded in how clinical, operational, network, and financial teams actually depend on one another.
How do you handle security, compliance, and PHI?
We operate within your existing security framework, under BAAs for any engagement touching PHI. Our governance design covers privacy, access controls, model risk management, and the audit trails healthcare regulators expect.
Find the few AI bets that pay
A 30-minute working session. We'll walk through what an engagement could look like.
Value proven. Value delivered. Outcomes realized.